A child’s weight, length or height, head size, body-mass index and pubertal pattern become meaningful when they are measured accurately and compared over time. By the end, you will know what happens at different ages, how to read growth-chart trends, and when a change calls for repeat measurements, clinical assessment or referral.
Key takeaways
- Track weight, length or height, and head circumference against earlier measurements.
- Judge growth by its pattern over time, not one percentile alone.
- Discuss crossing percentile lines, poor weight gain, or stalled height promptly.
- Keep growth reviews during puberty to assess physical development and overall health.
What a growth-monitoring visit measures at each age
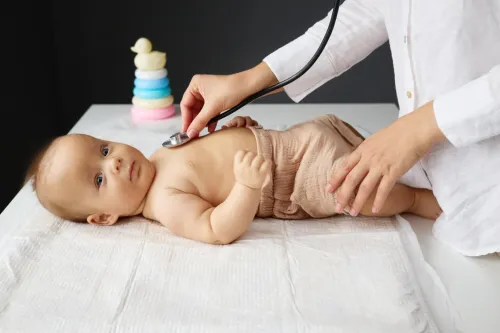
A newborn growth check records weight, length while lying down, and head circumference measurement, then compares them with birth data and age-based standards. The clinician also examines feeding, hydration, jaundice, heart and lungs, abdomen, hips, muscle tone, and general alertness.
- In early infancy, expect an infant weight and length using a calibrated infant scale and length board, plus head circumference. The clinician reviews feeding, vomiting, stools, sleep, development, and physical signs of illness.
- From about 6 months to 2 years, weight, recumbent length, and head circumference are repeated with the same technique where possible. The examination includes development, nutrition, and physical findings that could affect growth.
- From age 2, expect weight, standing height measured without shoes on a stadiometer, and body-mass index (BMI). The clinician checks blood pressure from age 3, using a correctly sized cuff, and reviews vision, hearing, development, and general health.
- During school years, serial standing height, weight, BMI, and blood pressure show whether growth is continuing steadily. The clinician also examines the spine, posture, thyroid, nutrition, and signs of chronic illness.
- In adolescence, the visit adds pubertal staging, height acceleration, body-composition changes, menstrual or sexual-health history, mood, sleep, and exercise or eating concerns.
Measurements are plotted by age and sex. WHO Child Growth Standards commonly cover birth through 5 years, with CDC charts commonly used from 2 through 19; switching systems can falsely change a percentile.
How clinicians use growth charts without overreading a percentile
A percentile is a position, not a health score. Clinicians plot each measurement against an age- and sex-specific reference, then compare several points to judge growth velocity and direction. A child who stays near the 3rd percentile may be growing well; a child at the 75th percentile may need review if growth slows.
- In the United States, clinicians commonly use the WHO Child Growth Standards from birth through 23 months and CDC growth charts from age 2 through 19 years. Switching chart systems can create an apparent percentile shift without any real change in growth.
- Weight is plotted with length in infants and toddlers as weight-for-length, while BMI is plotted by age and sex from age 2 onward.
- Head circumference is plotted separately in infancy and early childhood; a sudden rise or slowing pattern can require evaluation rather than being dismissed as a weight issue.
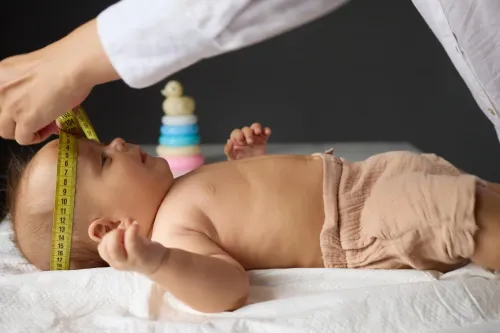
Technique determines whether the plotted point is trustworthy. Measure infants lying down on a length board, measure older children standing without shoes, and weigh with minimal clothing. Repeating measurements with the same equipment and method prevents a small positioning or clothing error from looking like genuine growth change.
Clinicians also compare the pattern with family height, nutrition, health history, and development. One unusual point usually prompts a recheck; a sustained change across measurements carries more meaning than a single percentile ranking.
What a changing growth pattern can reveal
A fall in growth velocity or a drop across two major percentile lines deserves attention, but not an automatic diagnosis. Repeat the measurement using the correct technique and, when possible, the same equipment; a small positioning or clothing error can mimic growth faltering.
- Repeat measurement when the change is unexpected, the child is unwell, or the result conflicts with earlier records. Confirm weight, length or height, and head growth before interpreting the trend.
- Arrange a nutritional review for poor weight gain, weight loss, feeding difficulty, restricted eating, or a weight decline that precedes slowing length or height. Review intake, vomiting, diarrhoea, constipation, food insecurity, and mealtime behaviour.
- Consider testing when confirmed faltering persists or accompanies diarrhoea, abdominal pain, fatigue, recurrent infections, excessive thirst, or other signs of systemic illness. Possible causes include malabsorption such as coeliac disease, chronic disease, and endocrine disorders.
- Refer to a pediatric specialist when height velocity remains low, weight is relatively preserved while height falls, or the child has marked short stature, disproportionate body measurements, or suspected skeletal or endocrine disease.
- Assess for stunting when length or height stays substantially low over time, rather than labeling a child from one low percentile. A stable child near the 3rd percentile may be healthy, especially when family heights support that pattern.
A growth review also needs parental heights and pubertal timing. Delayed puberty can explain later acceleration, while markedly early, late, or absent adolescent height acceleration warrants evaluation rather than reassurance from a single chart point.
Why monitoring remains important during puberty and adolescence
Puberty compresses major changes in height, weight, muscle, fat distribution and sexual maturation into a limited period. A single adult BMI cutoff or one height measurement can miss a problem during the adolescent growth spurt, while a serial, age- and sex-specific record shows whether change is on track.
- BMI-for-age identifies weight patterns against peers of the same age and sex. It supports childhood obesity screening, but it does not measure body fat directly; muscle, puberty, body proportions and the direction of change affect its meaning.
- Blood pressure requires an age-, sex- and height-based interpretation. A reading that looks acceptable by adult standards can be high for a younger teenager, and repeated elevation can signal cardiovascular, kidney or metabolic risk.
- Height acceleration shows whether the expected growth spurt is occurring. Little acceleration, a sudden slowdown or a sharp increase deserves review alongside nutrition, chronic illness and pubertal development.
- Body composition changes normally during puberty, but the balance of lean tissue and fat differs by sex, maturation stage and training. Weight alone cannot distinguish healthy muscle gain from excess fat or inadequate nutrition.
- Pubertal timing matters because early puberty, markedly uneven development or delayed puberty can reflect an endocrine, nutritional or chronic-health concern. The sequence of changes matters as much as the calendar age.
Bring up rapid weight change, stalled height, absent expected pubertal signs or distress about body shape at the visit. The clinician can compare measurements over time and choose observation, focused testing, nutrition support or referral rather than label your teenager from one number.
How to make routine growth reviews useful for your child
Bring the last few height, weight and head-circumference measurements, vaccination and medical records, medication details, and a short list of concerns. Add the heights of both parents, family history of late puberty or growth conditions, and notes on appetite, diet, bowel symptoms, sleep, activity and puberty-related changes.
Use the visit to turn an unexpected pattern into a plan:
1. Confirm the measurement. Ask whether height was taken with a stadiometer, weight with minimal clothing, and head circumference with a correctly placed tape. A repeat measurement can expose an equipment or positioning error.
2. Put the number in context. During pediatric growth monitoring, the clinician should compare serial measurements, growth velocity, family stature and pubertal timing, then perform an examination. BMI is a screening measure, not a body-fat measurement or diagnosis; muscle, puberty, body proportions, ethnicity and medical history affect its meaning.
3. Agree on the next step. Depending on the pattern, this could be a nutrition review, a planned recheck after a defined interval, blood tests, or a specialist referral. Ask what change would require an earlier review.
4. Record the plan. Note the next appointment date, symptoms to watch, and any feeding or activity changes. Dr Samutirika Dinesh Pediatrician Ecr can use this information to make a growth assessment based on the child, not a chart alone.
Related service
“GROWTH” is an increase in size of the body and organs, referring to the physical maturation of the body. View service → |
Frequently asked questions
What does a child growth-monitoring visit measure?
Clinicians measure weight, length for children under two, standing height for older children, and head circumference in infancy. They also review feeding, development, health, and physical findings.
How should you interpret a growth-chart percentile?
A percentile compares your child with children of the same age and sex. Clinicians focus on the pattern across several measurements rather than treating one percentile as a diagnosis.
What can a changing growth pattern reveal?
A change can point to feeding difficulties, illness, medication effects, nutritional problems, or an underlying medical condition. The clinician interprets it alongside the examination and health history.
Why does growth monitoring matter during puberty?
Reviews track the timing and pace of height gain, weight change, and puberty milestones. They can identify delayed or unusually early development and support timely assessment.
How can parents make growth reviews more useful?
Bring vaccination and medical records, a list of medicines and supplements, recent concerns, and details about eating, sleep, activity, and puberty changes.