
A routine check involves more than weighing a child: the clinician measures growth, reviews health habits, discusses age-appropriate skills and decides whether any result needs closer attention. You will know what happens at each stage, how to read the measurements without overreacting to one percentile, and what follow-up questions to ask before you leave.
Key takeaways
- Bring your child’s medicine list, allergy details, and recent health concerns.
- Growth percentiles show patterns over time, not a pass-or-fail result.
- Clinicians assess language, movement, learning, behaviour, sleep, feeding, and social skills.
- Ask what follow-up is needed, when it should happen, and who will arrange it.
What happens from check-in to the first measurements?
1. At check-in, the clinician confirms your child’s age, birth history, and reason for the visit, then asks about current concerns, medicines, recent illness, feeding, sleep, and allergies. This initial review helps place the routine child check-up in context before measurements begin.
2. For accurate child growth measurements, remove shoes and bulky clothing and use a calibrated scale for weight.
Infants and toddlers under about 2 years have recumbent length measured lying flat, with the head held against the fixed headboard and the legs gently straightened; older children have standing height for children measured without shoes, with heels together and the head positioned level.
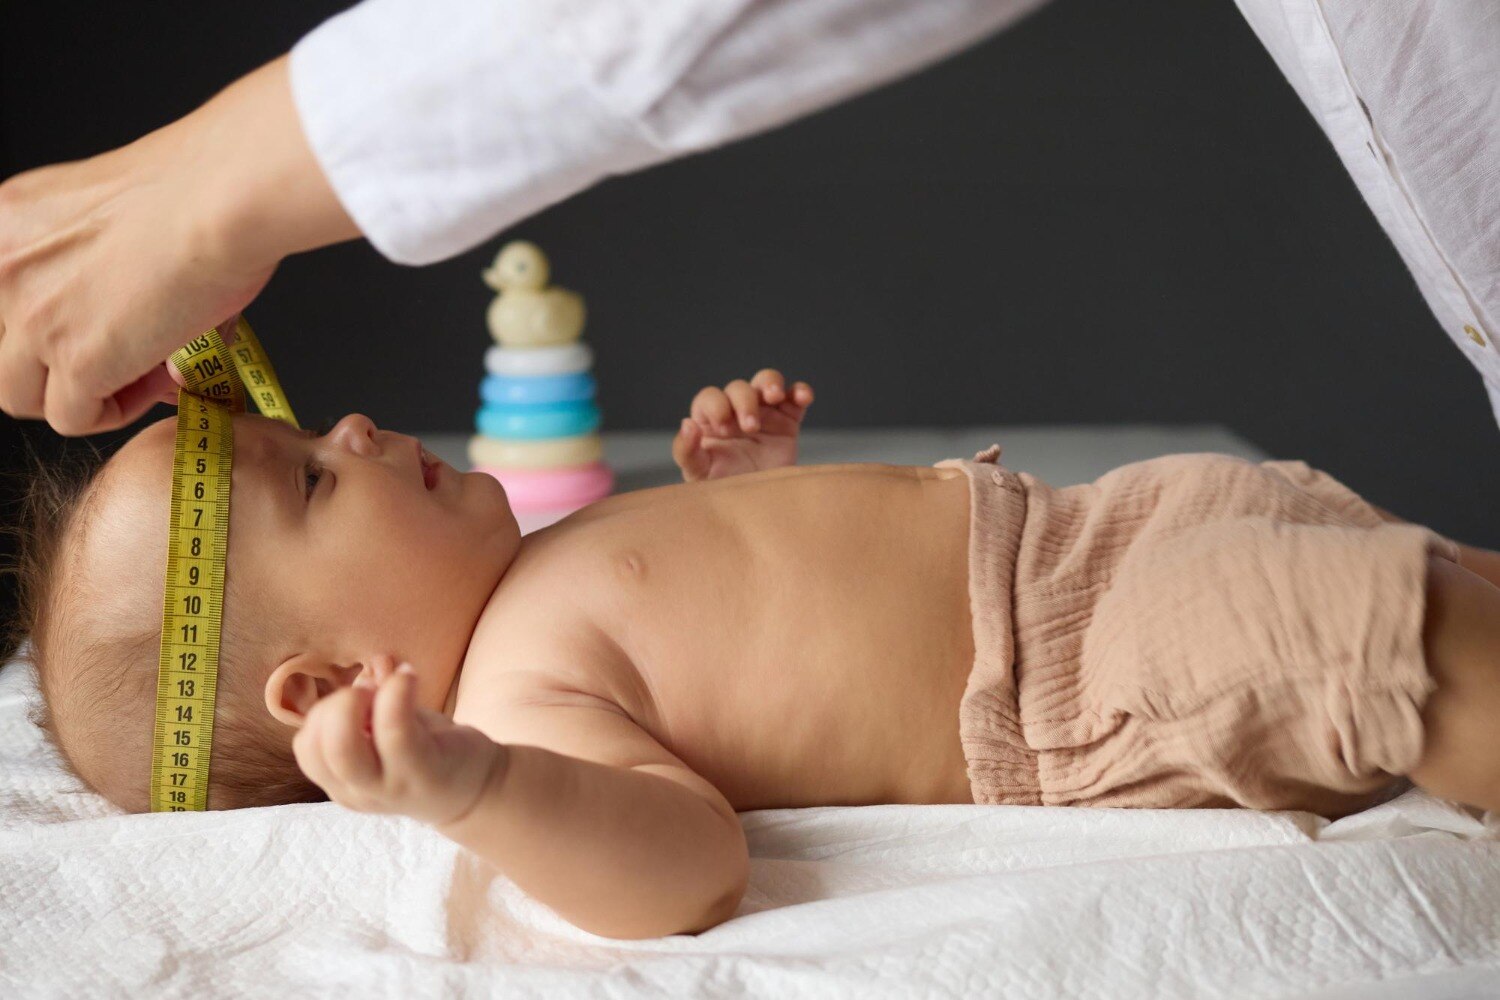
3. Staff measure head circumference in infants and young children with a non-stretch tape around the largest part of the head: above the eyebrows and ears, and around the most prominent part of the back of the skull. They also record vital signs.
Blood pressure is part of routine care from age 3, with earlier checks for prematurity, kidney disease, diabetes, obesity, or medicines that affect pressure.
Vision and hearing checks depend on age and cooperation. The visit may include an eye chart, instrument-based vision screening, otoacoustic emissions, or pure-tone audiometry. An abnormal screen usually leads to repeat testing or formal evaluation rather than an immediate diagnosis.
How are growth charts and percentiles used?
Measurements become useful when plotted, not viewed as isolated numbers. Weight, length or height, and usually head circumference through age 2 go onto age- and sex-specific charts. Length is measured lying down; height is measured standing.
| Chart or measure | What it compares | Common use |
|---|---|---|
| WHO Child Growth Standards | Children under 5 against a standard growth pattern | U.S. children younger than 2 and other settings using this reference |
| CDC growth charts | U.S. children ages 2–19 against reference data | U.S. children from age 2 through adolescence |
| National reference chart | Children against an appropriate national population reference | Practices following their country’s guidance |
Growth percentiles compare your child with children of the same age and sex; they are not grades. A healthy child can be at the 5th or 95th percentile, so the trend across several visits matters more than either number.
A notable shift across percentile lines deserves review, especially alongside feeding problems, repeated illness or slowed development. One unusual measurement does not establish a diagnosis, but a persistent change needs context.
For corrected age for premature babies, subtract the weeks born early from chronological age when interpreting early growth and development. Ask which age the clinician used and whether it is documented.
What will the clinician ask and observe about development?
1. The clinician begins with developmental surveillance: an ongoing conversation about birth weight, gestational age, feeding pattern, current diet, sleep, bowel habits, illnesses, medicines, activity and family heights. Tell them what your child does at home, including anything that seems difficult or different from before.
2. The clinician may watch your child interact, move around the room and respond to you.
They review language, gross motor and fine motor skills, social-emotional development and self-help: an infant’s head control, reaching, babbling and social response; a toddler’s walking, pointing, simple directions, words and self-feeding attempts; a preschooler’s speech clarity, jumping, drawing, cooperative play and dressing attempts; and an older child’s school functioning, friendships, independence and emotional regulation.
3. Developmental surveillance is different from developmental screening. Surveillance uses your report, the clinician’s observations and health history; developmental screening uses a validated questionnaire or instrument at specified ages. CDC child development milestones checklists describe what at least 75% of children do by an age, so they start a conversation rather than diagnose a condition.
4. Raise a concern even if the checklist looks reassuring. A missed skill, lost skill or caregiver concern deserves discussion and may lead to a formal assessment or referral instead of waiting for the next routine screening age.
What else is covered in a preventive growth visit?
A preventive child health visit can cover nutrition, sleep, physical activity, oral health, safety, emotional or behavioral health, and more than milestones. An immunization review compares the record with the current age-based schedule, identifies doses due and catch-up needs, and discusses vaccines due later.
A routine check does not guarantee that a vaccine will be given that day.
| Age group | Topics clinician may cover | Practical focus |
|---|---|---|
| Infants | Feeding and safe sleep | Breast milk or formula intake, starting solids, and placing the baby on the back on a firm, flat sleep surface |
| Children | Nutrition, sleep, activity, oral health and safety | Eating patterns, movement, brushing teeth, injury prevention and emotional or behavioral concerns |
| Adolescents | Sleep patterns, nutrition, substance use, mood and mental health | Daily routines, risk assessment, depression concerns, anxiety and support at home or school |
Vision and hearing screening is not a diagnosis. An abnormal eye-chart, instrument-based vision, otoacoustic-emissions or pure-tone result usually leads to repeat testing or formal evaluation.
Adolescent confidential care may include private time without a parent. The clinician explains confidentiality and its limits, then shares only information needed when there is immediate safety risk, abuse or serious risk of harm.
What happens when a result needs follow-up?
A follow-up plan should state what was reassuring, what needs checking, who will do it, and by when. One unexpected measurement does not automatically establish a diagnosis, but a persistent pattern, crossing percentile lines, developmental regression or a caregiver concern should not wait for a distant routine visit.
| Finding | Possible next step | Time frame |
|---|---|---|
| Growth measurement differs | Repeat weight, length or height; review nutrition and family height patterns | Within weeks or at a specified date |
| Vision or hearing screen is abnormal | Repeat screening or arrange formal testing | Promptly, based on the result |
| Developmental concern | Use a validated developmental assessment and consider early intervention | Do not wait for the next routine screen |
| Several findings or medical symptoms | Complete laboratory tests or arrange a growth concern referral to a pediatric specialist | Clinician specifies urgency |
Before leaving, ask:
- Which growth chart and which age were used, including corrected age if your child was premature?
- What changed from the last visit?
- Which warning signs require an earlier call?
- When is the next pediatric follow-up appointment due?
Early intervention can support a child before a formal diagnosis is settled. Dr Samutirika Dinesh Pediatrician Ecr can help coordinate repeat measurements, referrals and preventive care, supporting continuity of pediatric care for families in Chennai rather than treating each assessment as an isolated visit.
Frequently asked questions
What happens before my child’s first measurements?
At check-in, the clinician confirms your child’s age, birth history, and reason for the visit, then reviews concerns, medicines, recent illness, feeding, sleep, and allergies.
How are growth charts and percentiles used?
The clinician records measurements on age- and sex-specific growth charts and looks at your child’s pattern over time rather than treating one percentile as a diagnosis.
What does a clinician assess during a development check?
The clinician asks about and observes skills such as movement, language, learning, behaviour, social interaction, feeding, and sleep.
What else is covered during a preventive growth visit?
The visit can include a physical examination, vaccinations, nutrition and safety guidance, oral-health advice, sleep review, and screening based on your child’s age and history.
What happens if a result needs follow-up?
The clinician explains the finding, recommends the next step, and gives you a timeframe for review, further screening, referral, or testing.





